SS-31: caring for your cells' battery
SS-31: cuidar la batería de tus células
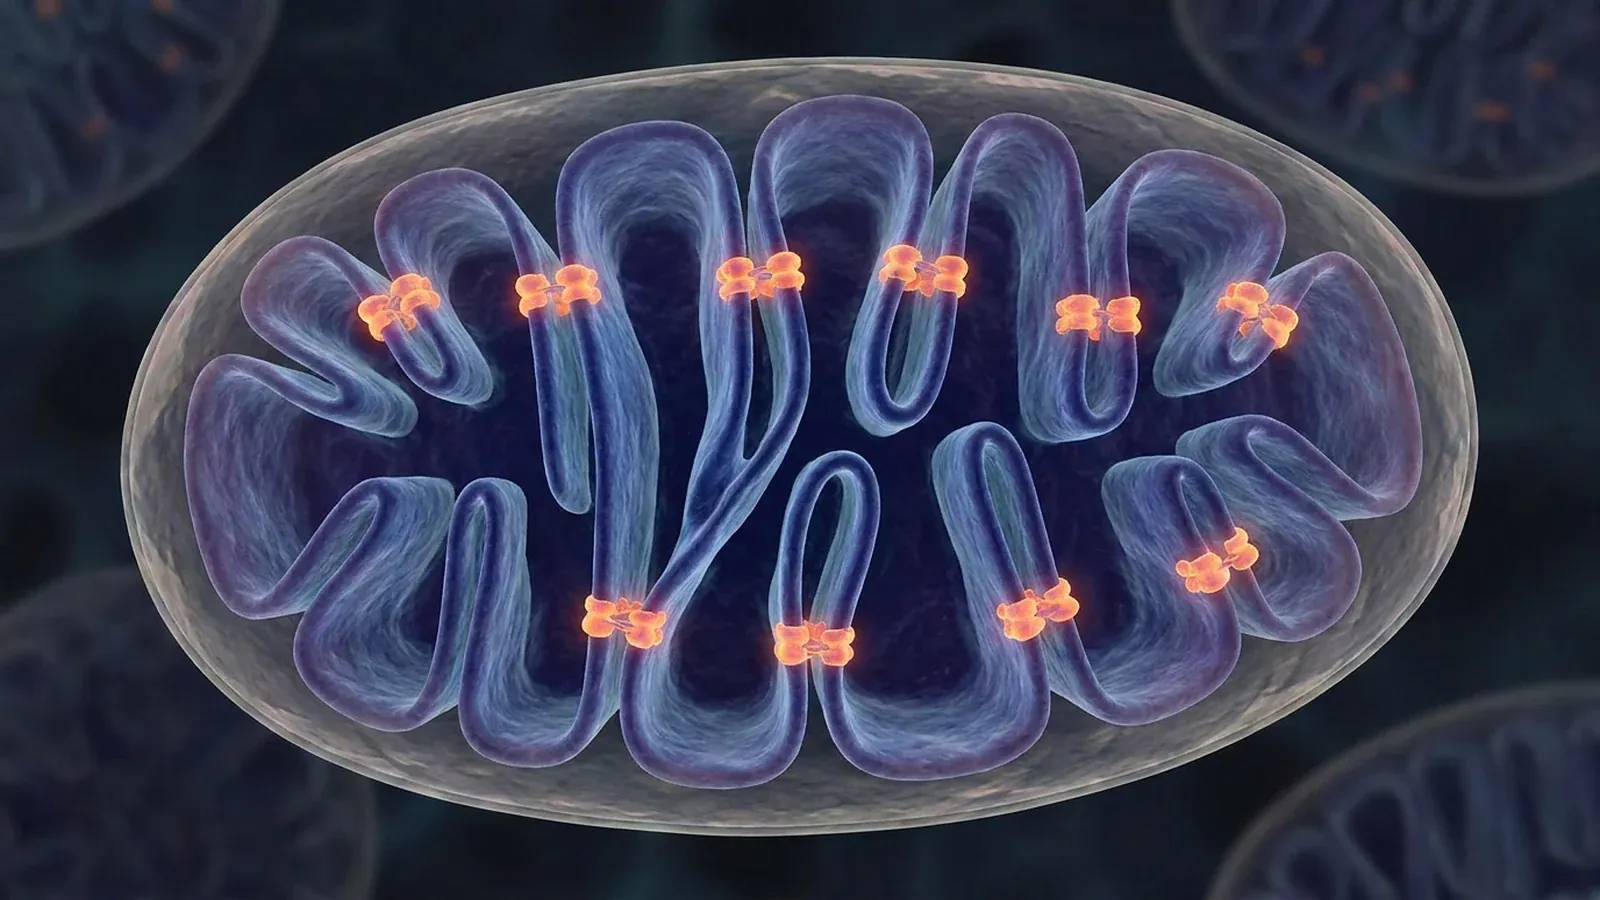
Inside every one of your cells there are tiny structures that make almost all the energy you use — to think, to walk, to keep your heart beating. They're called mitochondria.
And they have a beautiful design detail. Their inner membrane isn't smooth: it's folded like an accordion, into tight folds called cristae. Those folds multiply the surface area where energy gets made. More folds, more energy.
What holds those folds in shape is a very particular fat, almost unique to that one place in the body: cardiolipin.
And here's the good news. There's a small molecule that binds to that fat and helps keep the folds in shape. It's called SS-31. And in September 2025 it stopped being an experiment: the FDA approved it as a medicine.
The essentials in 30 seconds
- SS-31 — also called elamipretide — is a synthetic peptide of just four amino acids. Tiny, and designed to enter the cell and find one single site.
- That site is cardiolipin, the fat that holds the folds of the mitochondrion's inner membrane in shape.
- It doesn't add energy from outside. It helps the structure that makes energy keep its shape, which is not the same thing.
- On September 19, 2025, the FDA granted accelerated approval as FORZINITY™ for Barth syndrome, an ultra-rare genetic disease. It is the first mitochondria-targeted medicine ever approved.
- In that program, eight patients reached 168 weeks of continuous treatment — more than three years of safety data.
- There are 29 clinical studies registered on ClinicalTrials.gov. That is far more scrutiny than almost any peptide receives.
- In healthy older adults with poorly functioning mitochondria, a single dose raised muscle energetic capacity measured by magnetic resonance — the first documented case of reversing mitochondrial dysfunction in vivo with a drug.
- That same measurement was back to baseline at seven days, and fatigue resistance didn't improve. We're telling you anyway, because it marks where we actually stand today.
- The most common finding across studies was injection-site discomfort.
What you'll read
- Why the shape of a mitochondrion matters so much
- Cardiolipin: the scaffold of the folds
- What SS-31 actually does
- From experimental molecule to approved medicine
- Three years of data in Barth syndrome
- The big trial that missed, and what it taught
- What has been tested in healthy aging
- How it relates to MOTS-c
- How well it's tolerated
- So your expectations are the right ones
- Who is this NOT for?
- Frequently asked questions
- How we offer it
- Sources
Why the shape of a mitochondrion matters so much
Almost everyone learned in school that the mitochondrion is "the powerhouse of the cell." True, but it undersells it, and it loses the interesting part.
A mitochondrion has two membranes, one inside the other. The outer one is smooth. The inner one is folded into cristae, and living in those folds are the molecular machines that turn what you eat and the oxygen you breathe into ATP, your body's energy currency.
Here's the key: those machines work better when they're packed close together and well organized in the folds. The geometry isn't decoration. It's part of the mechanism.
When the folds flatten or lose their order, energy production drops even with plenty of fuel and oxygen available. And flattened cristae show up in a wide range of situations: interrupted blood flow, certain genetic diseases, and also — more gently and more slowly — in aging muscle.
That leads to a very practical idea. If the problem is one of shape, maybe the answer isn't pushing in more fuel, but helping the structure hold its shape.
Cardiolipin: the scaffold of the folds
Cardiolipin is an unusual fat. It has four tails instead of the usual two, and that cone shape lets it settle into the tight curves of the folds, like a wedge holding up an arch.
It lives almost exclusively in the inner mitochondrial membrane. It's one of the clearest signatures of that particular place in the body.
It does three things at once:
- Holds the curvature of the cristae.
- Clusters the machines of the respiratory chain so they work close together.
- Anchors cytochrome c, a protein that shuttles electrons through the system.
That last point has a known trap in it. When a mitochondrion is under stress, cytochrome c changes jobs: instead of shuttling electrons, it starts oxidizing the cardiolipin right next to it. And as cardiolipin degrades, the folds lose their scaffold. The structure comes apart on its own, and the more it comes apart, the faster it comes apart.
If you want to interrupt that loop, the place to act is fairly obvious.
What SS-31 actually does
SS-31 is a synthetic peptide made of four amino acids. Its design has two uncommon features: it can cross cell membranes without needing a transporter, and once inside it concentrates in the inner mitochondrial membrane.
There it binds cardiolipin. It doesn't consume it or replace it — it associates with it reversibly.
A 2013 paper in the Journal of the American Society of Nephrology showed in detail what happens next. In a model of interrupted blood flow, binding cardiolipin inhibited cytochrome c's peroxidase activity — the vicious loop above — and sped up ATP recovery once blood flow returned.
Seven years later, a study in PNAS asked the question in reverse: which proteins does this molecule end up next to inside the mitochondrion? The answer was tidy. Every protein that showed up is a cardiolipin binder, and they fall into two groups: those in the chain that produces ATP, and those in 2-oxoglutarate metabolism.
It's a reassuring result precisely because it's boring. Fifty scattered targets across the cell didn't appear. Exactly the neighborhood the mechanism predicted did.
From experimental molecule to approved medicine
This is where SS-31 separates itself from the rest of the peptide catalogue, and it's worth saying plainly.
On September 19, 2025, the FDA granted accelerated approval to elamipretide (brand name FORZINITY™) for the treatment of Barth syndrome in adults and pediatric patients weighing at least 30 kg.
Barth syndrome is an X-linked genetic disease that primarily affects males. An estimated 150 people in the United States carry the diagnosis. The affected gene, TAFAZZIN, is the one responsible for finishing the job of building mature cardiolipin. Without it, cardiolipin stays half-made and the mitochondrion works badly — with serious consequences for the heart and skeletal muscle.
In other words: the first disease where this molecule was approved is exactly the cardiolipin disease. The mechanism and the approval tell the same story.
Two necessary clarifications, because the distinction matters.
First: accelerated approval means the FDA authorized the medicine based on a measure that predicts benefit, with a commitment to keep studying it. It's a real and serious pathway, and it's also a conditional one. A new phase 3b/4 trial in Barth syndrome has in fact been recruiting since July 2026.
Second, and more important for whoever is reading this: the approval is for Barth syndrome. It is not an approval for aging, for tiredness, or for athletic performance. What the approval demonstrates is that the molecule works well enough, at the right site, with an acceptable safety profile, for a regulatory agency to let it onto the market. That is already far more than most peptides can say.
Three years of data in Barth syndrome
The study that opened the door is called TAZPOWER. It started as a randomized, double-blind, placebo-controlled crossover trial — each patient received both, at different times — over 28 weeks. Twelve people with genetically confirmed Barth syndrome took part.
Twelve people sounds like almost nothing. In absolute terms it is. But the number deserves context: if there are roughly 150 people with the disease in the entire country, twelve patients is a very large fraction of everyone who exists.
After the trial came the part that produced the most information: a 168-week open-label extension, published in Genetics in Medicine in 2024. Ten patients entered and eight reached the end.
What was measured over those 168 weeks: safety and tolerability as the primary endpoints; and as secondary endpoints, six-minute walk distance, a disease-specific fatigue scale, muscle strength, echocardiographic parameters, and cardiolipin biomarkers.
The published results describe significant improvements sustained over time and good tolerability, with injection-site reactions the most frequent adverse event.
Holding up through three years of daily treatment in a progressive disease, with most participants completing follow-up, says two things: that the medicine is tolerated, and that the people receiving it had reasons to keep going.
The big trial that missed, and what it taught
We'll tell you about what didn't work too, because it's the only way you can judge the rest.
MMPOWER-3 was a phase 3, randomized, double-blind, placebo-controlled trial in adults with genetically confirmed primary mitochondrial myopathy. Twenty-four weeks of treatment. Results published in Neurology in 2023.
It did not meet its primary endpoints. Neither six-minute walk distance nor the fatigue score showed a significant benefit over placebo in the full group.
That's the honest headline. But the story doesn't end there, and what came next is interesting.
"Primary mitochondrial myopathy" is not one disease: it's a set of diseases with different genetic causes. Some come from mutations in mitochondrial DNA; others from mutations in nuclear DNA. And a prespecified subgroup — the nuclear-DNA one — did show improvement in walk distance, while the mitochondrial-DNA group showed no difference.
A later analysis published in Orphanet Journal of Rare Diseases in 2024 explored that finding to understand who was responding and to design the next trial better. Out of it came NuPower, a phase 3 dedicated exclusively to nuclear-DNA mutations, with 102 participants, which finished its main phase in 2024.
- The right reading: the big trial taught that mixing different diseases into one group can hide a real effect in part of them.
- The wrong reading: treating a subgroup analysis as if it were proof. It isn't. It's a hypothesis that has to be tested separately — which is exactly why NuPower was run.
What has been tested in healthy aging
Here we get to the question that probably brought a lot of people to this article, and it deserves a direct answer.
There is a trial. It's small, it's well done, and it produced a genuinely notable result.
It was published in PLOS ONE in 2021. Thirty-nine healthy adults aged 60 to 85 took part, selected precisely because their mitochondria were functioning poorly. It was randomized, double-blind and placebo-controlled. Magnetic resonance and optical spectroscopy — no biopsy needed — were used to measure muscle energetic capacity.
After a single two-hour infusion, muscle energetic capacity rose relative to placebo. The authors themselves described it as the first demonstration of a pharmacological intervention able to reverse mitochondrial dysfunction in vivo, immediately after treatment, in aging human muscle.
That's a real finding and worth celebrating. Now the rest of the picture, which matters just as much:
- At seven days there was no longer a difference from placebo. That fits the molecule's short half-life in blood: the effect is reversible, not cumulative.
- There was no improvement in fatigue resistance in the muscle studied. Raising a measured capacity and noticing that you tire less did not turn out to be the same thing in this trial.
- It was a single dose. Nobody yet knew what repeated dosing does in healthy older people.
That last question is exactly the one being answered now. An open-label phase 2a pilot study, started in late 2025 in older adults, is evaluating a daily subcutaneous dose. No results have been published yet.
So the honest position today is this: the solid human evidence is in primary mitochondrial disease and Barth syndrome, not in healthy aging. In aging there's a real signal, measured with good instruments, waiting to be confirmed with sustained treatment.
How it relates to MOTS-c
If you read our guide on MOTS-c, you may notice both talk about mitochondria. They work in very different ways and it's worth not mixing them up.
| MOTS-c | SS-31 | |
|---|---|---|
| Where it comes from | Written by your own mitochondrial DNA | Synthetic |
| What it does | Travels out as a metabolic signal | Stays inside, bound to cardiolipin |
| Human trials | None published | 29 registered; one FDA approval |
That last row is the one that carries the weight. We like the MOTS-c mechanism and we've written it that way, but set side by side, only one of them has been through a regulatory agency.
How well it's tolerated
After more than a decade of studies and thousands of doses in people with different conditions, the pattern is consistent and fairly clean.
By far the most frequent are injection-site reactions: redness, itching or local discomfort. It was the most common adverse event both in the three-year Barth syndrome extension and in the mitochondrial myopathy studies.
It's given as a daily subcutaneous injection in the sustained-treatment studies. Its half-life in blood is short, which explains both the daily schedule and why the effect measured in the older-adult study was gone within a week.
Being well tolerated doesn't mean harmless in any context. It means that in the populations studied, under medical supervision, the profile turned out to be manageable.
So your expectations are the right ones
None of this contradicts the good news above. It just puts it in its place.
The approval is for Barth syndrome. The sustained results that exist were measured in people with mitochondrial disease. Nobody can promise you the same if your situation is different.
In healthy aging what exists is a single-dose signal, measured with good instruments and still unconfirmed with continuous treatment. It's a promising starting point, not a conclusion.
And the time frame matters. This is not a "take it and notice it Tuesday" molecule. In the programs where it's been studied, the thinking is in months and the evaluation is by measurement, not by sensation.
What is reasonable to expect from us: that a physician looks at your case and tells you frankly whether this makes sense for you, or whether there's a path with more evidence behind it.
Who is this NOT for?
- If you're looking for immediate energy. Sleeping well, eating real food, and treating anemia or a low thyroid do more for your energy, and can be verified with labs.
- If you're pregnant, trying to conceive, or breastfeeding.
- If you have a serious undiagnosed condition — marked fatigue is a symptom that deserves an explanation before it gets a treatment.
- If you have active cancer or are in cancer treatment. Anything acting on mitochondrial metabolism has to go past your oncologist first.
- If you have significant kidney or liver disease. Not an automatic no; a reason for a physician to review the whole case.
- If you expect it to replace strength training. Exercise is still the only thing that increases the number of mitochondria in your muscle, and there's no shortcut around it.
- If you expect a visible change in the mirror. This doesn't work there.
Frequently asked questions
Is SS-31 FDA approved?
Yes, and it's worth saying precisely: the FDA granted accelerated approval on September 19, 2025 for Barth syndrome, in adults and pediatric patients weighing at least 30 kg. It's the first mitochondria-targeted therapy approved. It is not approved for aging, fatigue or performance.
Will it give me more energy?
In the older-adult study it raised the measured energetic capacity of muscle after a single dose, but it did not improve fatigue resistance. Those are two different things and the trial separated them carefully. Promising you'll feel more energetic would go past what the data show.
Why are you telling me about the trial that missed?
Because without it you'd have no way to judge the rest. And because MMPOWER-3 taught something useful: grouping different diseases together can bury a real effect in part of them. That lesson changed the design of the next trial.
Is it the same as NAD+ or MOTS-c?
No. Three different things that happen to share a neighborhood. NAD+ is a working molecule of metabolism; MOTS-c is a signal that leaves the mitochondrion; SS-31 stays inside, bound to cardiolipin, holding the structure.
How long before I notice anything?
There's no established time frame outside the conditions studied. In the programs where it's been studied, follow-up happens over months and with objective measurements. If someone promises results in days, they're making it up.
What if my labs come back normal?
Then that's good news, and a serious physician will tell you so instead of selling you something. Sometimes the best next step is a different one: sleep, strength training, thyroid, hormone health, or supervised weight management.
How we offer it
We wrote this article with one fixed idea: that by the time you got here you'd have the full picture — what's approved, what failed, and what's still being studied — and could decide for yourself.
Yes, we offer SS-31. And how we offer it matters more to us than the product.
Once you start your program, a licensed physician reviews your case — habits, stress, sleep and medical history — and orders labs only if they consider it necessary. Depending on your medical history and condition, the clinician may schedule a video consultation with you if they consider it necessary.
From there:
- Prescription. This is Rx. Not a supplement, not a bottle from the internet.
- Licensed pharmacy. They prepare your order, with their chain of custody and their controls.
- Shipped straight to your home, in two days.
- Care team available for your questions.
- Recurring deliveries and dose adjustment with an optional monthly check-in.
- Cancel whenever you want, in one click.
And if reviewing your case shows that a different route makes more sense for you, we'll tell you even when it doesn't suit us. We have clinically supervised weight management and hormone health programs, and GLP-1 programs with FDA-approved medications (Wegovy®, Foundayo™, Ozempic®) from $149 a month, by telemedicine, in Spanish and English.
Eligibility is determined by medical evaluation. Individual results vary and are not guaranteed.
Sources
Articles located through PubMed. Trial status verified on ClinicalTrials.gov.
- Birk AV, Liu S, Soong Y, et al. The mitochondrial-targeted compound SS-31 re-energizes ischemic mitochondria by interacting with cardiolipin. J Am Soc Nephrol. 2013;24(8):1250-1261. 10.1681/ASN.2012121216
- Chavez JD, Tang X, Campbell MD, et al. Mitochondrial protein interaction landscape of SS-31. Proc Natl Acad Sci U S A. 2020;117(26):15363-15373. 10.1073/pnas.2002250117
- Reid Thompson W, Hornby B, Steele S, et al. Long-term efficacy and safety of elamipretide in patients with Barth syndrome: 168-week open-label extension results of TAZPOWER. Genet Med. 2024;26(7):101138. 10.1016/j.gim.2024.101138
- Karaa A, Bertini E, Carelli V, et al. Efficacy and Safety of Elamipretide in Individuals With Primary Mitochondrial Myopathy: The MMPOWER-3 Randomized Clinical Trial. Neurology. 2023;101(3):e238-e252. 10.1212/WNL.0000000000207402
- Karaa A, Klopstock T, Goldstein A, et al. Genotype-specific effects of elamipretide in patients with primary mitochondrial myopathy: a post hoc analysis of the MMPOWER-3 trial. Orphanet J Rare Dis. 2024;19(1):432. 10.1186/s13023-024-03421-5
- Roshanravan B, Liu SZ, Ali AS, et al. In vivo mitochondrial ATP production is improved in older adult skeletal muscle after a single dose of elamipretide in a randomized trial. PLoS One. 2021;16(7):e0253849. 10.1371/journal.pone.0253849
- Sabbah HN, Tian Y, Gupta RC, et al. Elamipretide: A Review of Its Structure, Mechanism of Action, and Therapeutic Potential. Int J Mol Sci. 2025;26(3):944. 10.3390/ijms26030944
- U.S. Food and Drug Administration. Accelerated approval of FORZINITY™ (elamipretide HCl) for Barth syndrome, September 19, 2025.
Related articles
Your trust is worth more than a sale.
This article is informational and is not medical advice. SCTS1 does not prescribe medications. All medical care, prescriptions and treatment plans are provided by licensed physicians through our partner platform, and preparations are dispensed by licensed pharmacies. Eligibility is determined by a licensed provider. Elamipretide (SS-31) is FDA approved only for Barth syndrome; any other use is off-label and is a decision for a licensed physician who evaluates your case. Individual results vary and are not guaranteed.